Bridging the Valley of Death

How huMannity works with investors to move neurotech from promise to product
The gap the market won’t finance
Plenty of promising neurotechnologies never make it to patients. The science works, but the money isn’t available, or it doesn’t last. Somewhere in the long gap between invention or discovery and a company that venture capital will fund, the program stalls and quietly dies. The industry has a name for that gap: the “valley of death”. For the past 40 years, huMannity Medtec has functioned to get innovative technologies across it.
We take on programs earlier than an institutional investor comfortably could, then carry them through the often expensive, middle stretch (product development, early clinical work) until the risk is something professional capital can price. By the time you see one of our programs, the early translational work is finished, and IP is developed. What’s left is a valuable asset.
Our non-profit advantage
huMannity is a not-for-profit organization with no equity or shareholders. This structure enables us to work in the part of the development pipeline venture capital is usually forced to skip.
What it really means is no fund-clock ticking toward a forced sale before a technology is ready. Less return mandate dictating which programs we pursue and which we don’t. No daylight between our interests and a partner’s. Because we’re funded by our own past exits, the capital doesn’t expire, it doesn’t need to be distributed to LPs or shareholders, and we can stay with a hard problem for as long as it takes to solve. Most organizations in this space need outside money just to start, but we’ve usually done the hardest part before the first pitch.
“That’s actually where we live. We take on early-stage ideas that venture doesn’t touch because it’s too risky, too early, too far away from commercialization — and we carry it to a point where venture will be interested.”
— Brian Mech, VP of Strategy
Four ways we partner
No two assets are the same so we are flexible in our partnering models. We pick the structure that fits the technology in front of us and the needs of our partners. Generally, we partner in 4 distinct ways, each with their own advantages:
The spinout is our conventional model. We develop an asset in-house, de-risk it to a first-generation product with early clinical validation in humans, then spin out a dedicated company, recruit its management team, and co-invest alongside the venture syndicate. We don’t disappear once the company is standing; we hold equity and stay involved until it has outgrown us.
The asset sale transfers a program straight to a strategic buyer. No cap table, no IPO, no Series A, no standalone company to build. When the right acquirer already exists, and our program solves a need that they have, it’s the shortest line from technology to market.
The build-to-buy puts our development infrastructure and our financial capital to work on a program in a space where we hold real expertise, structured around a predefined exit at an agreed valuation. For a strategic that wants a product without carrying development risk and costs on its own financial statements, it offers rare certainty on both timeline and economics.
And licensing hands a venture-backed company a running start. We make our technology and IP available so a partner doesn’t have to design a system from scratch, and we’ll often co-invest alongside them.
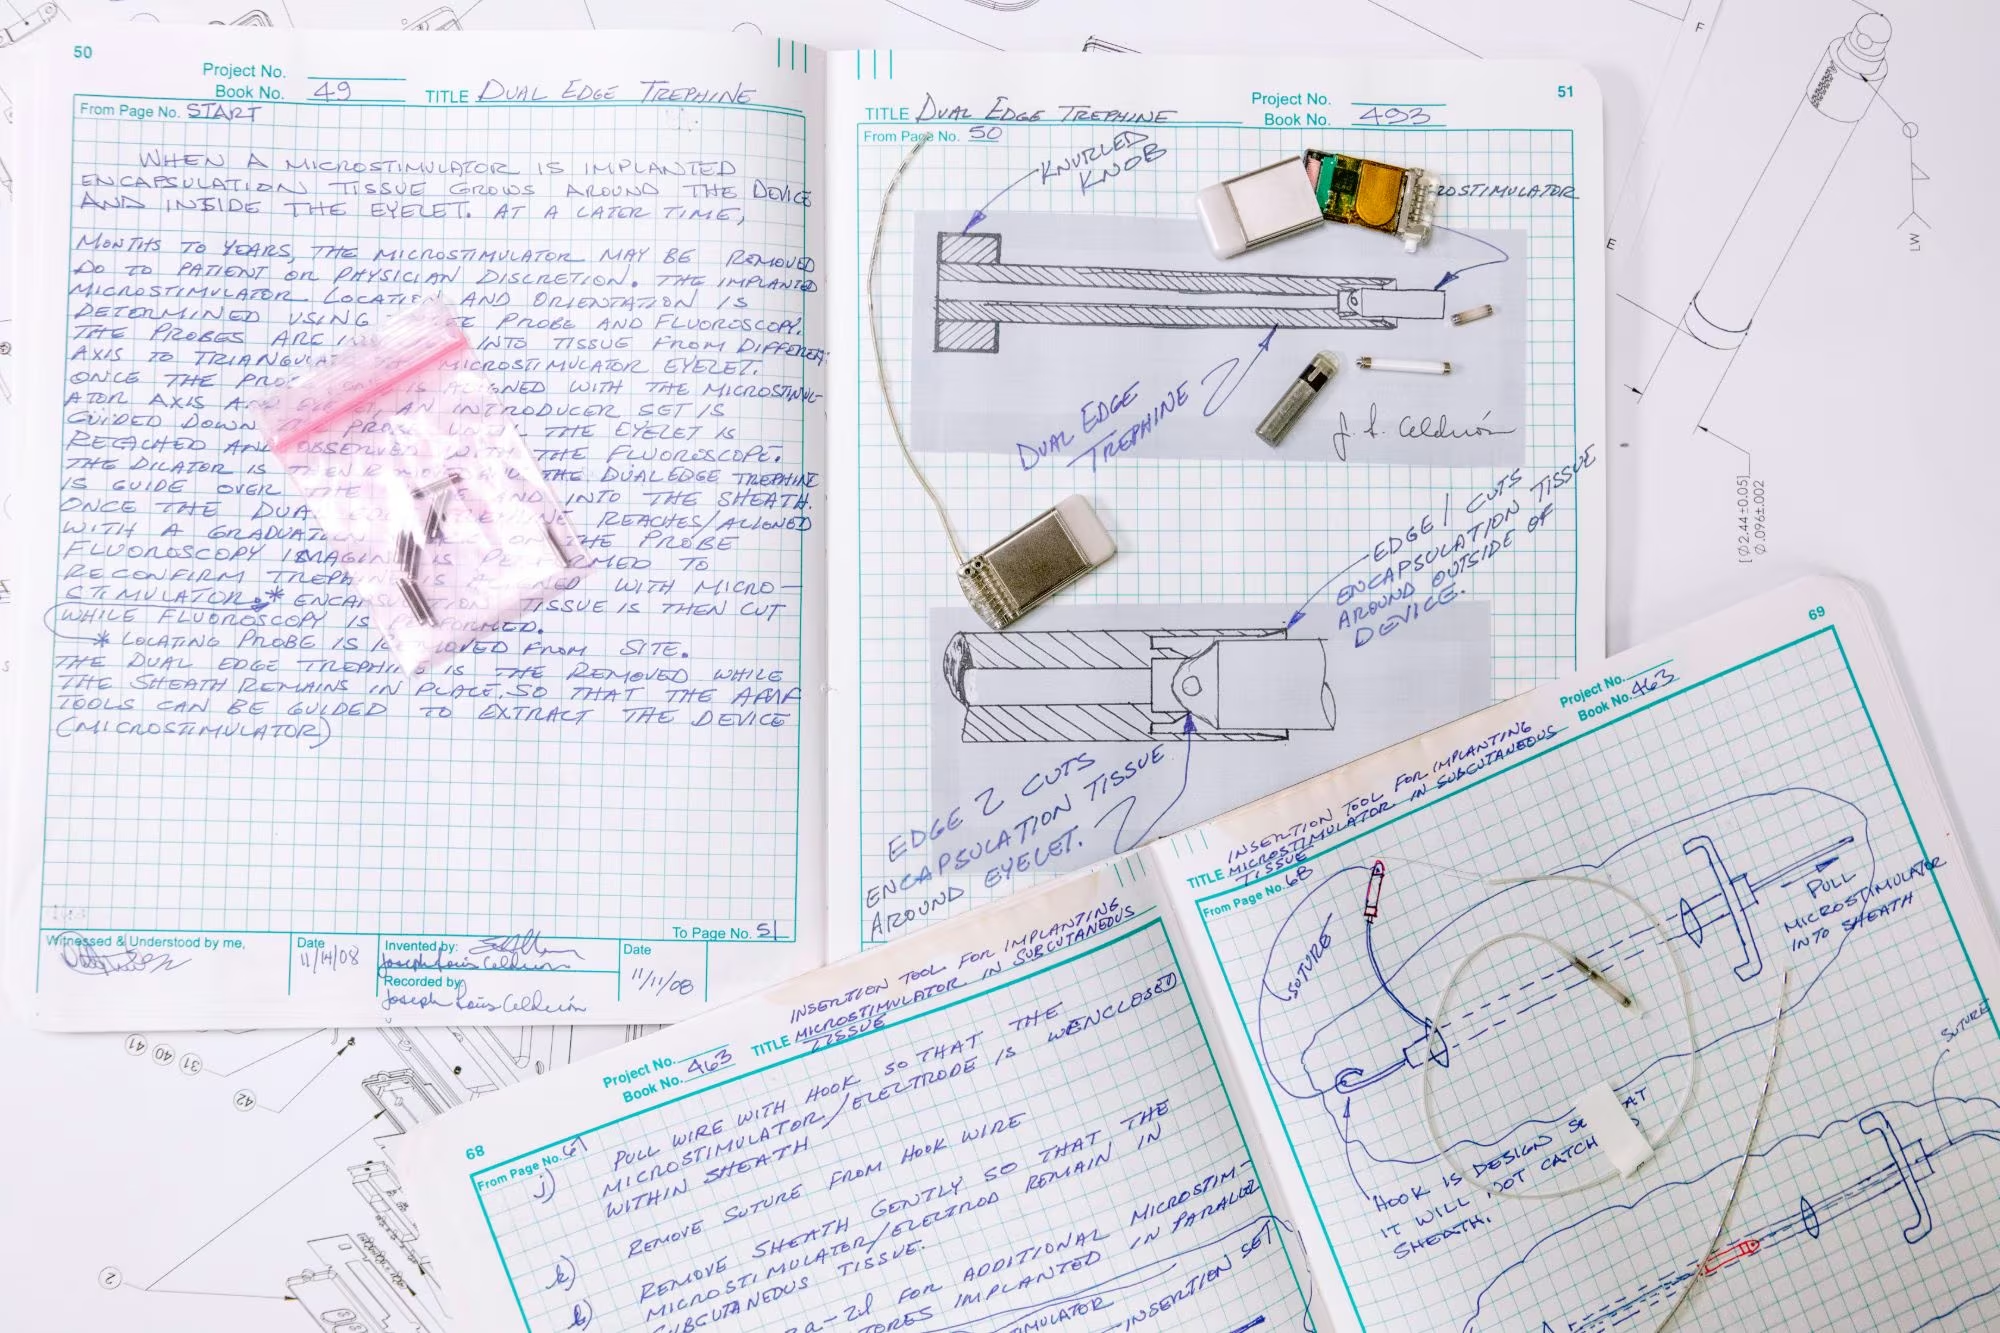
The partnership models above are one way that we work with venture capital. We’re also limited partners in several venture funds, less for the financial returns than for the proximity. It allows us to build relationships with potential future investors, identify areas of unmet need, and occasionally access ideas that are too early for their own mandates.
“We’re LPs primarily for strategic reasons. It allows us to build relationships with potential future partners while supporting the early-stage medtech ecosystem. We only got started in this 5 years ago, but it is already yielding dividends. ”
— Brian Mech, VP of Strategy
A track record that compounds
None of this is just a pitch-deck exercise. Over four decades, our programs have produced roughly $10 billion in spinoff value, and most recently a $3.7 billion exit.
Axonics, a leader in sacral nerve stimulation for pelvic floor disorders is the latest example. We built the technology in-house, spun out the company, brought in its management team, and were its only investor in the early going. It went public in 2018, won PMA approval, and sold to Boston Scientific for $3.7 billion in 2024. Medallion, an implantable pump company, took a different route, a straight asset sale to Medtronic. And the engine hasn’t stopped; HYPNOS, our obstructive sleep apnea program, is in first-in-human trials in Australia right now, and iVEAcare, which licensed our platform in 2024, closed a Series A backed by Vensana, Treo, Hatteras, and huMannity, and is about to raise their Series B.
Where huMannity fits
Depending on where and how you invest, huMannity can be a few different things to you. A source of clinical-stage assets and programs nearing exit. A co-development partner on a build-to-buy. Or the technical muscle behind an early concept that needs real derisking before it's fundable.
The structure changes, but our stake in the outcome doesn’t. We hold equity. We put our own money in. We stick around as long as we are needed. Most development shops hand off a technology and move on the moment it changes hands. We stay on the cap table, exposed to the same asset, until it reaches the outcome you're underwriting.
We're comfortable engaging early, before the picture is fully clear. So if there's a project in your portfolio that stalled somewhere in development, or a white space you would fund if someone else carried the early risk, that's the conversation huMannity is built for.